Fibroids FAQ's
Uterine fibroids are benign lumps that grow in the uterus. Almost 50% of women will get uterine fibroids by the age of 50. These are benign (non-cancerous) lumps but can lead to symptoms that can affect the quality of your life.
The exact cause of fibroids is not known, but they are more common in Afro-Caribbean women. Fibroids usually grow slowly and can sometimes reach impressive size even up to the size of a full term pregnancy!
Fibroids are oestrogen-dependent and therefore are uncommon before the age of 20 and tend to shrink after menopause.
Fibroids are known to cause period-related symptoms. Heavy periods, intermenstrual bleeding and fatigue due to anemia are common symptoms. With increasing size, fibroids can be felt as a tummy mass and can press on the bladder leading to frequency and urgency of micturition. Sometimes, they outgrow their own blood-supply and can become painful.
Ultrasound scan is the best way to detect size and location of uterine fibroids.
Treatment depends on size and location of fibroids and symptoms caused. Asymptomatic fibroids can be left alone.
- Management of symptoms: to reduce heaviness of periods and treat anaemia
- Hysteroscopic resection: Suitable for intra-cavity (submucous) fibroids
- Laparoscopic myomectomy: Suitable for fibroids up to 10cm in size
- Open myomectomy: Reserved for very large and numerous fibroids
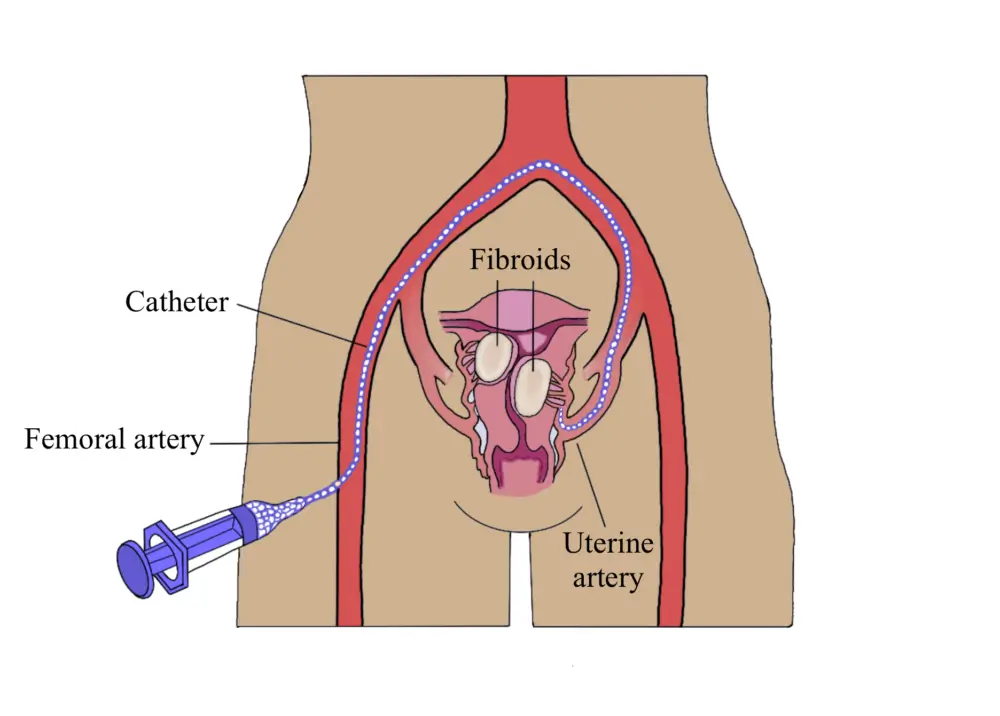
- Uterine artery embolisation: Treatment to block blood supply of fibroids leading to shrinkage
- MRI-guided focused ultrasound: New treatment useful for small-medium sized fibroids
- Hysterectomy (laparoscopic or open): A permanent solution suitable to women with severe symptoms who have completed their family
Very often, fibroids can be treated by key-hole surgery. If the fibroids are encroaching into the uterine cavity, they can be easily resected (hysteroscopic resection). Laparoscopic myomectomy is suitable for fibroids up to 10cm in size and usually 1-3 fibroids can be removed in one key-hole procedure. Finally, if hysterectomy is needed, it can be often performed as a key-hole procedure.
In presence of fibroids, pregnancy often progresses without any problems but it can also be a rocky relationship! Fibroids can make it more difficult to get pregnant and can also increase risk of miscarriage or premature delivery. You are more likely to have a breech presentation or transverse lie and need a caesarean section. Bleeding after delivery can also be a problem. See your doctor to see if removal of fibroids is necessary before getting pregnant.
This is very rare and is quoted as 1 in 1000. If the fibroids are growing at a very rapid rate, an MRI scan may be needed to obtain more information.
We offer a fibroids testing and monitoring package for self pay ladies. For further information about fibroids, visit our specialist website London Fibroids.
For support, visit the British Fibroid Trust a UK based voluntary not-for-profit patient support group run by volunteers, who provide balanced information to help people make informed choices on treatment.
Fortunately, fibroids do not usually interfere with chances of getting pregnant Most of the fibroids are small and do not interfere with the cavity of the uterus or the fallopian tubes.
Submucous fibroids (those which encroach on the uterine cavity) can sometimes affect the process of implantation. This can lead to sub-fertility and sometimes early pregnancy loss.
Fibroids in the upper corner of the uterus (cornual region) can occasionally obstruct fallopian tubes and can be a cause of tubal factor subfertility. Similarly, very large fibroids and an enlarged uterine cavity can be a cause of not getting pregnant.
So in general, if the fibroids are small (smaller than 6cm) AND if the cavity is normal AND if the fallopian tubes are patent (open), there is no cause to worry.
An ultrasound scan is usually all that is required. It can help in assessment of size, numbers and location of fibroids in relation to the uterine cavity and fallopian tubes.
Hycosy (HYstero-Salpingo COntrast SonographY) scan is where a contrast in injected into the uterine cavity and visualised on scan coming out of the fallopian tubes. This helps in more accurate assessment of uterine cavity and tubal patency.
Hysteroscopy is direct visualisation of uterine cavity with an endoscope. This is a gold-standard for assessment and treatment of submucous fibroids to normalise the uterine cavity. This procedure is called as TransCervical Resection of Fibroid (TCRF) or Hysteroscopic Myomectomy.
Laparoscopy can help in assessment of the fibroids in relation to the fallopian tubes and also feasibility for laparoscopic surgery.
Fibroids usually cause no problems with pregnancy but can sometimes be associated with risks during antenatal period, labour and post-partum.
Fibroids can increase the risk of early pregnancy loss and preterm birth especially if they are large or interfere with the uterine cavity (submucous fibroids).
Fibroids tend to increase in size with increased blood supply of pregnancy. This can lead to increased discomfort. Increase in size is also associated with ‘Red degeneration of Pregnancy’. This happens due to rapid increase in the size of fibroids where the central area of a fibroid does not get enough blood supply and undergoes ‘necrosis’. This is associated with pain and tenderness over the fibroid. Sometimes admission to the hospital and rest is required for pain relief, anti-inflammatory and supportive treatment.
Fibroids in the lower part of the uterus can lead to malposition such as transverse lie or breech presentation necessitating Caesarean Section. Caesarean Section can sometimes be difficult and complex due to location of the fibroids.
Post-delivery, fibroids can interfere with contraction of the uterus leading to post-partum haemorrhage.
A consultation with a gynaecologist with an ultrasound is often what is required to make an assessment. If the fibroids are found to be large or within the uterine cavity, further assessment or intervention may be necessary. Fibroids may be associated with anaemia and correction of iron levels may be required before embarking on pregnancy.
Resection of submucous fibroids (TCRF, Hysteroscopic Surgery) is associated with improved pregnancy outcome and there is no increase in risk during pregnancy or labour.
Myomectomy operation can sometimes mean that a natural labour and delivery may not be safe. Your surgeon will be able to advise you if an Elective Caesarean Section is required.


Other related conditions and treatments

Pelvic Pain Ultrasound Scan
A detailed pelvic ultrasound scan to investigate possible causes of pelvic pain.
Fibroid Ultrasound Scan
A specialist pelvic ultrasound scan to assess uterine fibroids, including size, number and location.
Fertility Ultrasound Scan
A fertility pelvic ultrasound scan and a follicle tracking ultrasound scan are commonly done before pregnancy, especially when assessing fertility or trying to conceive.

Robotic-Assisted Surgery

Robotic-assisted myomectomy
Minimally invasive technique allowing precise removal of fibroids with smaller incisions, reduced blood loss, and faster recovery. Book an appointment Call us When is robotic surgery…

Outpatient Hysteroscopy
As an outpatient procedure, an outpatient hysteroscopy is performed in a treatment room in the clinic and lasts between 5 and 30 minutes.

Hysterectomy
A hysterectomy is a surgical procedure to remove the uterus. It may be recommended to treat fibroids, heavy bleeding, endometriosis, or other gynaecological conditions. After a...

Open Myomectomy
Myomectomy (Myoma = fibroids, ectomy = removal) literally means surgical removal of fibroids. This is the procedure of choice for women who have symptomatic fibroids and...
Uterine Fibroid Embolisation
Uterine artery embolisation for fibroids is a minimally invasive procedure that involves blocking the blood supply to Uterine Fibroids, causing them to shrink and alleviate related...

Hysteroscopy procedure information and costs

Hysteroscopy
A hysteroscopy is an examination of the inside of the uterus (womb) using a fine telescope.

Laparoscopic Surgery
Laparoscopy is looking inside the abdomen with a telescope (laparos = abdomen, scopy = to have a look). This procedure is used to make a diagnosis...

Fibroids monitoring

Fibroids